20 May 2020 - Endocrine
1000-1015hr – Welcome, Jac’s trivia, reminder about recording and recap – Maria
1015-1100hr – CTB Brain interpretation – Daniel Nour (Radiology Registrar)
1100-1145hr – Endocrine Registrar Anojian Koneshamoorthy – Case Based discussion on Endo Emergencies
1145-1200 - Break
1200-1230 – Adrenal and Thyroid Emergencies – Khalid
1230 - 1300 - Electrolyte Problems - Matt
1300-1315hr – coffee/lunch break
1315-1345hr – ECG of the week/Gas of the week/Image of the Week – Jacqueline/Mark/Matt
(if time) 1345 – SAQs -Sarah/Jacqueline
1300-1500hr – Fellowship OSCE group - Brendan
1400-1500hr – Sarah B, Chris, Marrillo - Covid-ALS low fidelity SIMS/practice with Stu – tutorial room ED
Key Learning Points
Hyperglycaemic emergencies
DKA
Diagnostic criteria: hyperglycaemia (>11mmol/L) + ketosis + HAGMA
Cerebral oedema is the key life-threatening complication of DKA
When managing DKA, hypoglycaemia and hypokalaemia/hyperkalaemia are the other key complications
The general exam answer for how to manage DKA includes:
Resuscitate if shocked - attention to ABCs
Treat dehydration with balanced IV fluids (initially 1 litre in the first hour)
Treat hypokalaemia if < 5mmol/L
Commence short acting insulin at 0.1units/kg/hr. Aim to reduce BSL by 1-2mmol/hr
Once glucose < 15mmol/L, commence 5% glucose infusion at 100mls/hr
Seek and treat underlying precipitant such as antibiotics for infection
Supportive care: nurse 30 degrees head up, NBM, cardiac monitoring for arrhythmias
HHS
There are no specific diagnostic criteria. Patients tend to have BSL >30mmol/L, normal ketones, no acidosis, severe dehydration and osmolarity >320
Management includes:
Resuscitate
Treat dehydration cautiously. Na should not drop more than 10mmol in 24 hours
Insulin at 0.5units/kg/hr. Aim for BSL to drop by no more than 3mmol/L. Commence 5% glucose when BSL < 15mmol/L
Give thromboprophylaxis - these patients are at high risk of DVT/PE
Seek and treat underlying cause
Rapid Electrolyte Treatment Review
Hyperkalaemia in ALS: Give calcium for cardiac membrane stabilisation, then shift the potassium into cells (insulin, salbutamol, sodium bicarb), dialysis
Hypokalaemia: give potassium!
Hypercalcaemia: IV Fluids in the ED - other treatments under endocrinology
Hypocalcaemia: Give calcium gluconate.
Hypernatraemia: correct slowly with IV fluids
Hyponatraemia: hypertonic 3% saline if seizures or unconscious, then depends on cause of hyponatraemia (hypovolaemia, euvolaemia or hypervolaemia). Correct slowly! No more than 10mmol/24 hours
Adrenal and thyroid emergencies
Thyroid storm is a life threatening exacerbation of hyperthyroidism involving organ dysfunction. Clinical features include fever, diaphoresis, tachycardia, N/V/D and coma. Differential diagnoses include: sepsis, heat stroke, malignant hyperthermia, NMS, sympathomimetic toxidrome, drug withdrawal and pheochromocytoma.
Treatment includes:
Supportive
IVF
Cooling
Paracetamol
Propranolol 1mg IV boluses
Specific
Hydrocortisone 200mg IV QID
Propylthiouracil 1g PO then 250mg QID
Sodium iodide/potassium iodide or Lugol’s iodine after propylthiouracil
Myxoedema coma is the extreme life-threatening form of hypothyroidism.
Clinical features include stupor, hypothermia, respiratory failure and coma. These are on top of all the usual hypothyroidism clinical features.
Treatment includes:
Supportive
Resucitation, intubation, warming, IF fluids, acid base and electrolyte correction
Specific
Hydrocortisone
Replacement of thyroid hormones (controversial)
Treat underlying cause such as infection
Think of adrenal crisis (usually Addison’s) in the shocked patient that is not responding to treatment as you would expect. Classically they have hypoglycaemia, hyponatraemia and hyperkalaemia. If ever you see this on a blood gas think adrenal crisis.
Specific treatment is to give steroids - hydrocortisone 100mg IV Q6h
ECG of the Week
A 75 year-old man presented via ambulance with small volume PR bleeding. In the ambulance he was noted to have a recurrent, short-lived arrhythmia. He reports dizziness during these episodes which he has experienced without investigation for months. PMHx: Ischaemic heart disease and T2DM. Here is his ECG when he arrived in hospital. He was never unconscious and his only symptom was dizziness.
Findings of this ECG
Features: Regular broad complex tachycardia. Positive concordance of QRS complexes through praecordial leads. Two capture beats – normal morphology of these without evidence of STEMI on the leads that we can see. RSR’ complexes with a tall left rabbit ear. AV dissociation (p waves best seen in V1/V2)
Diagnosis: Most likely ventricular tachycardia based on ECG and clinical features (age, cardiac history)
Key learning point:
The differential diagnosis for a regular broad complex tachycardia include: VT, SVT with aberrancy (including WPW, atrial flutter with BBB, SVT with BBB), pacemaker mediated tachycardia and metabolic derangement such as hyperkalaemia and sodium channel blocker overdose
VT should always be assumed in the first instance.
Management of VT (conscious and stable)
Amiodarone 300mg IV (or 5mg/kg) over 20 minutes followed by 900mg over 24 hours
Alternatively can consider DCR
Other drug options include procainamide, lignocaine 1mg/kg or sotalol
Give Mg if long QT – in this case, amiodarone should probably be avoided and DCR utilised.
Management of shock resistant VT
This is largely an evidence free zone
Give Amiodarone after 3rd shock (as per ALS guidelines)
Can consider further amiodarone or lignocaine.
Continue effective CPR with routine ABCs and attention to reversible causes
Options then include
High-energy defibrillation with simultaneous shocks – i.e. use two defibs
Consider attenuating the symphathetic drive (stop adrenaline, use esmolol)
Isoprenaline if Brugada syndrome
ECMO CPR
Image of the week
A 25 year old female presented with 3/7 of pleuritic chest pain. She had a sinus tachycardia and pleural/pericardial rub on exam. PMHx: ? autoimmune condition that is currently being investigated. Click the images to enlarge
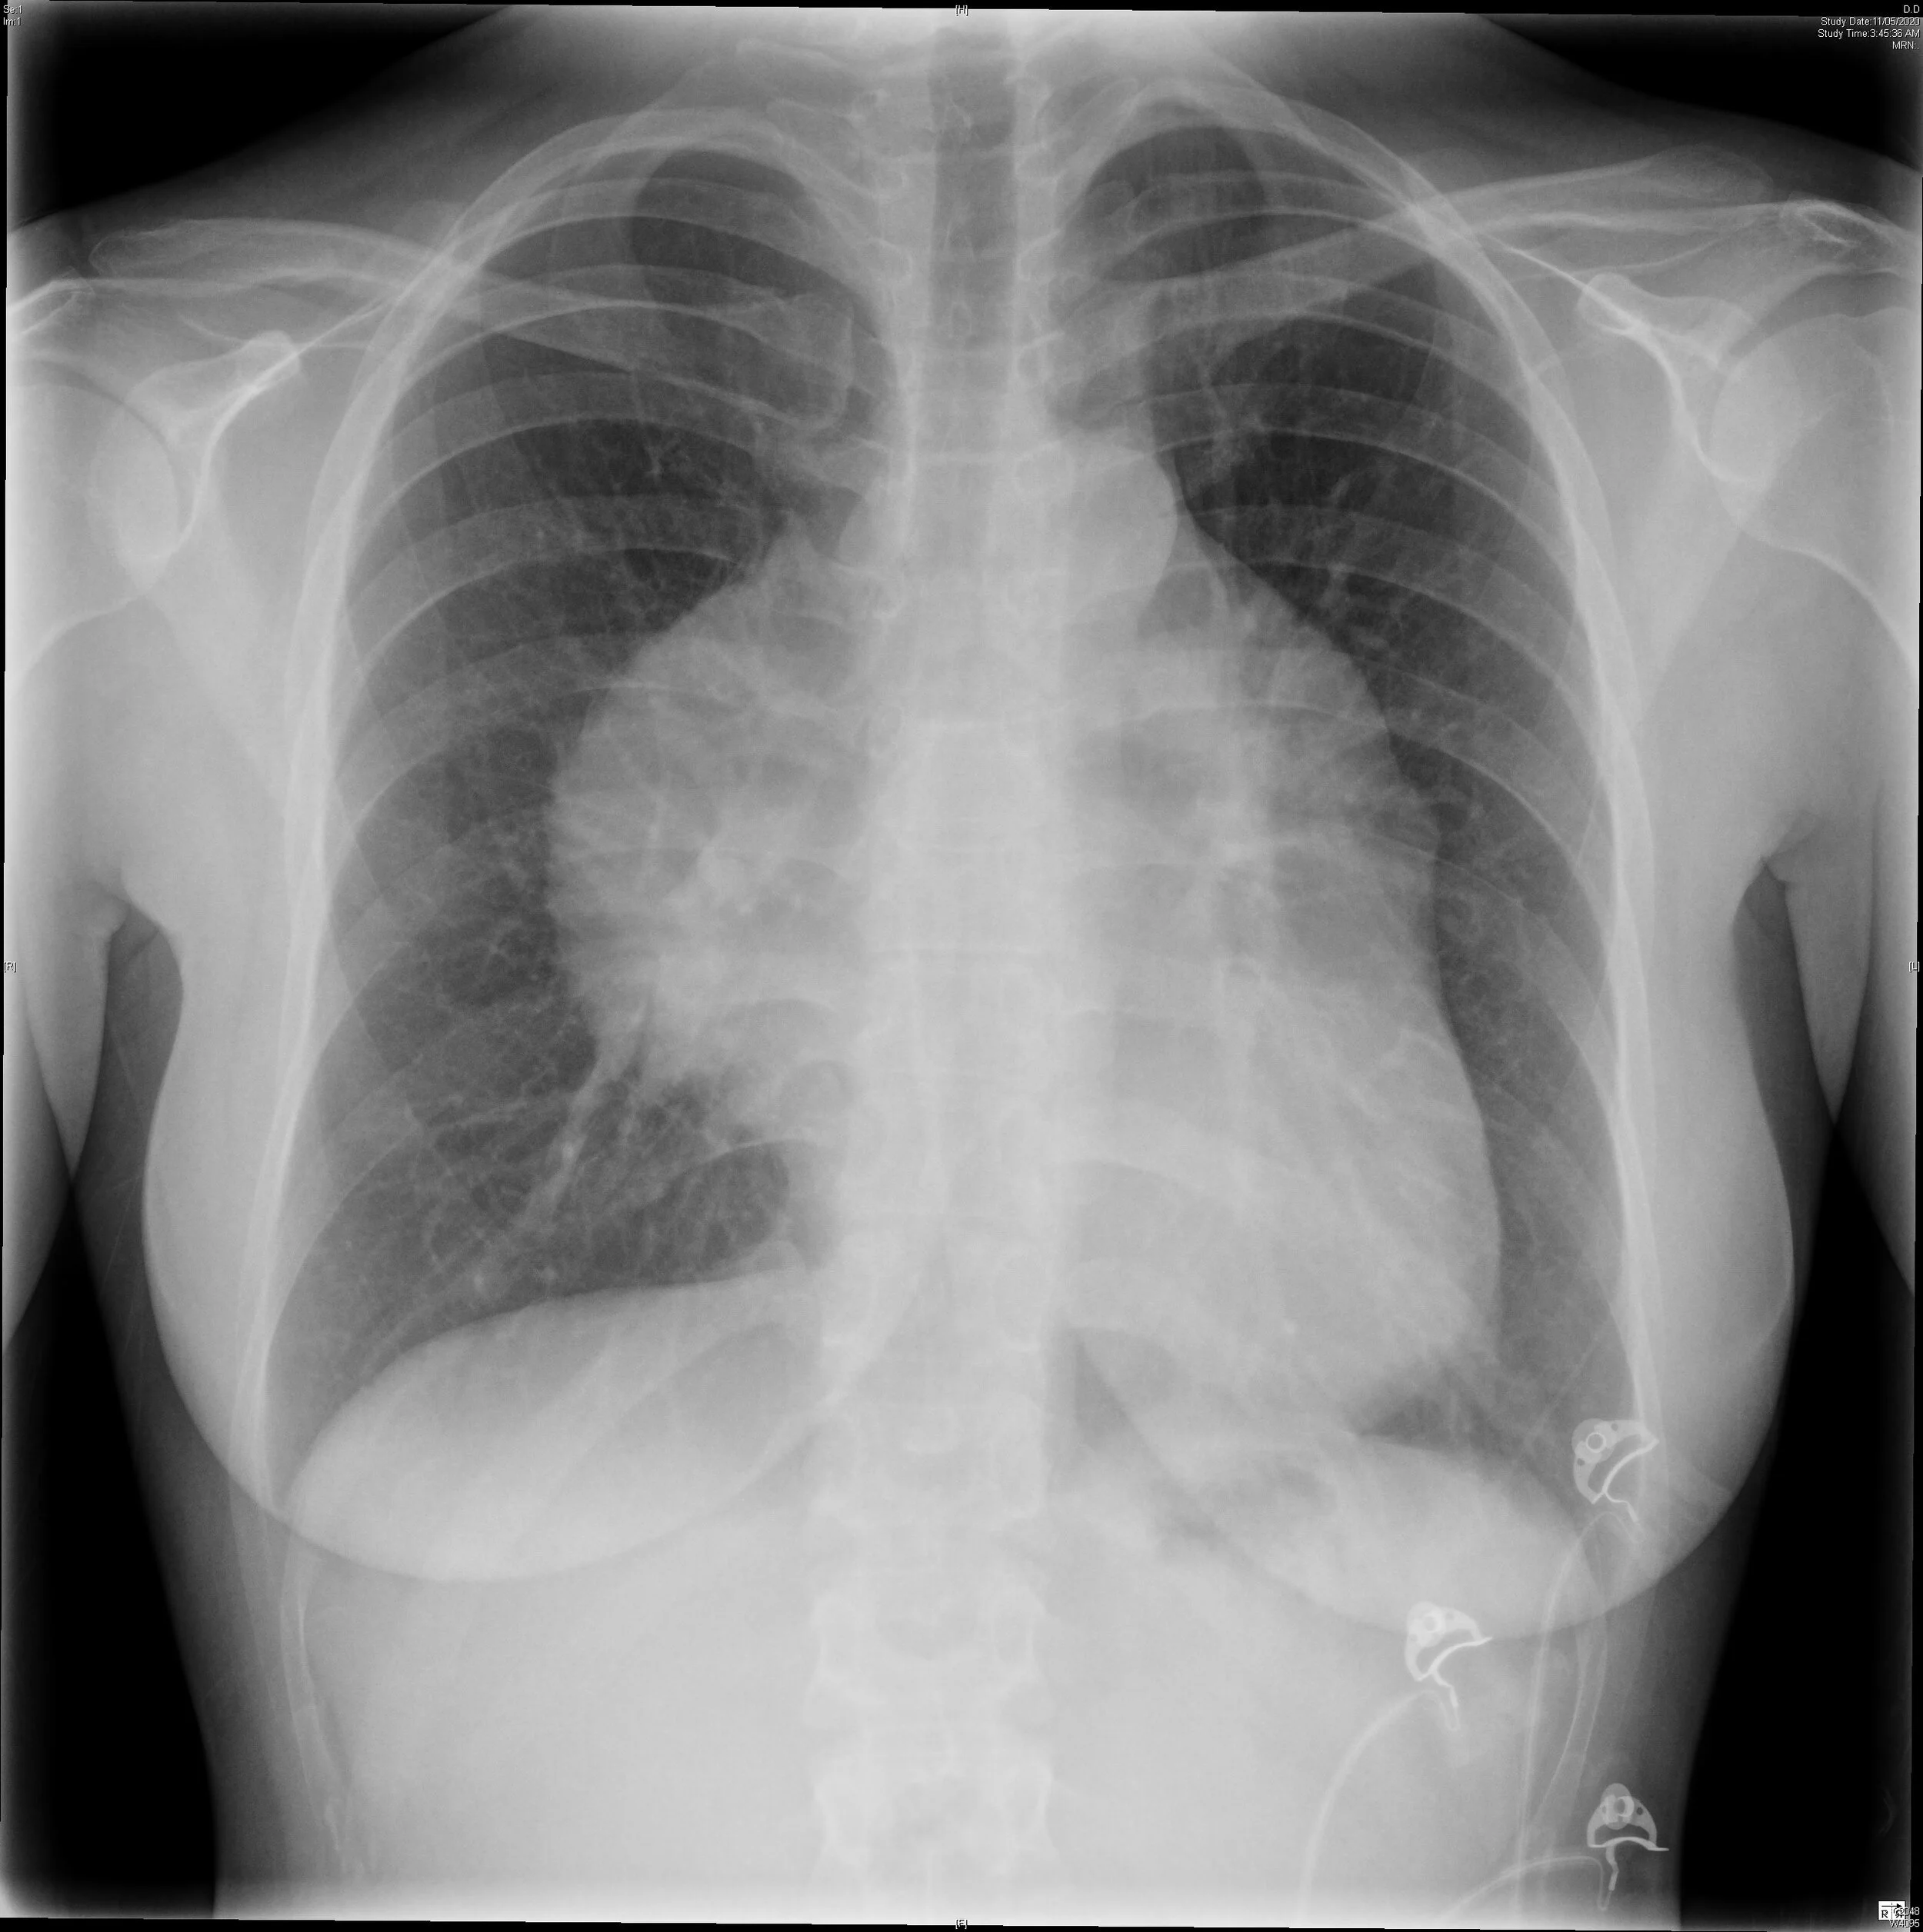
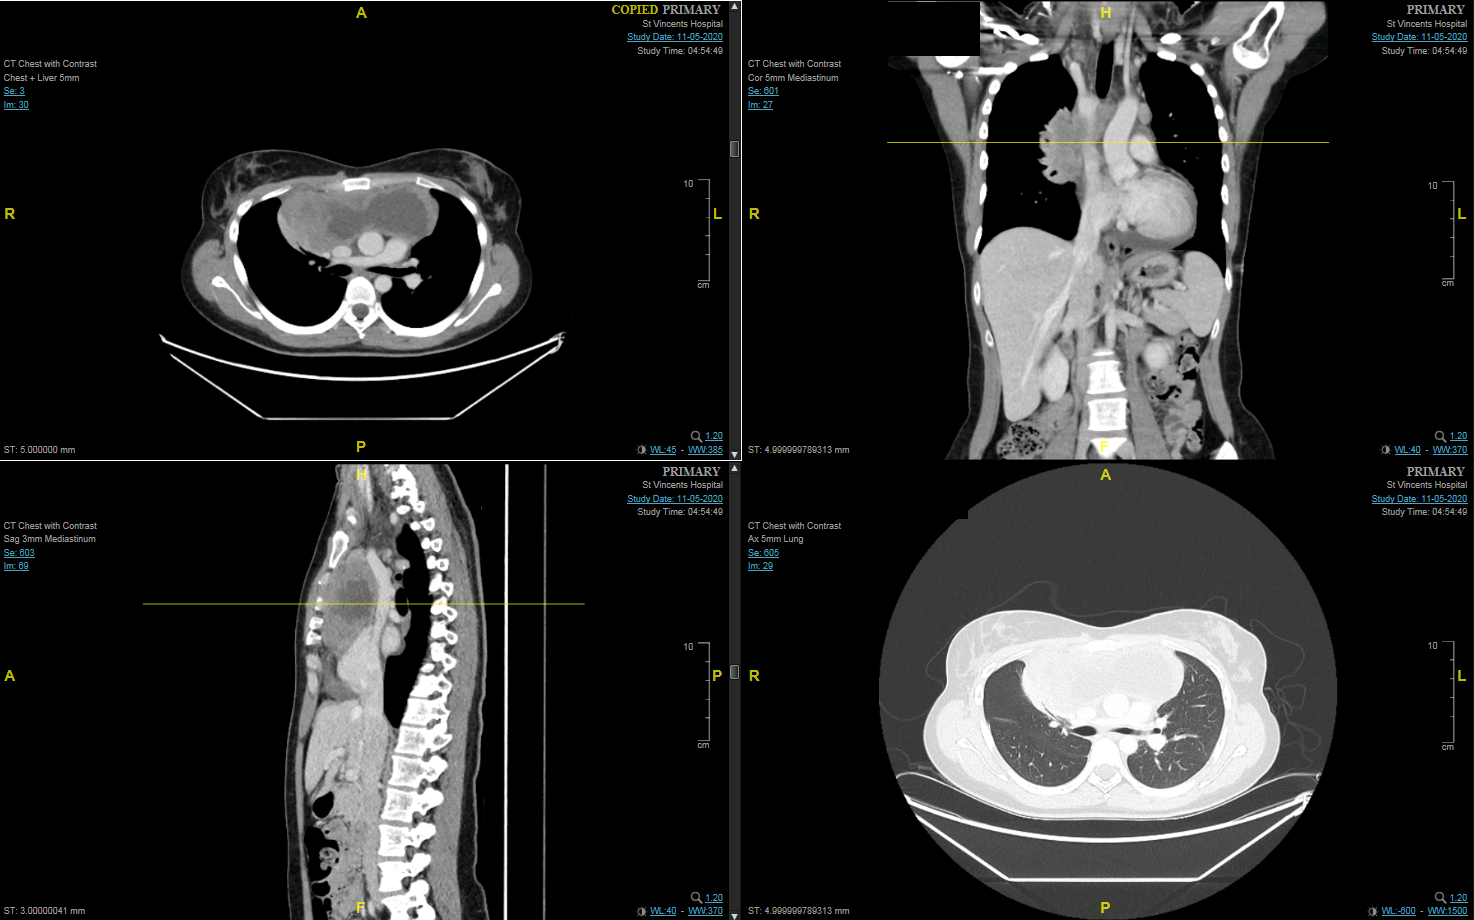
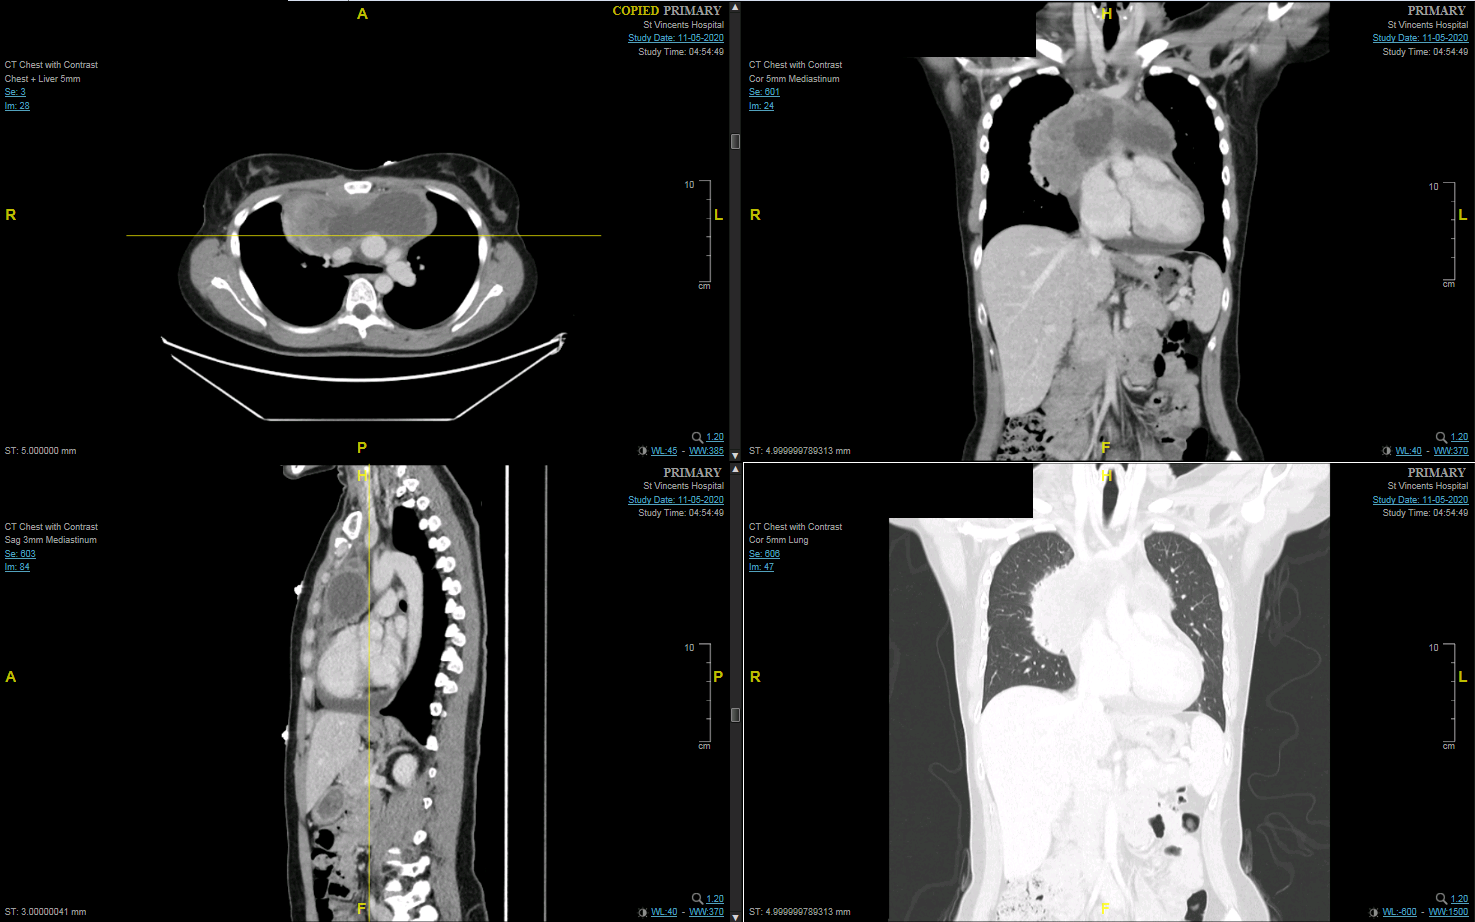
These images show a large anterior mediastinal mass. There is partial SVC obstruction and invasion and also a significant pericardial effusion. It turned out to be large lymphoma.
Matt discussed a rapid ED approach to chest CTs to identify life threats. These include:
Aorta and pericardium - is there a dissection? Is there pericardial fluid?
Saddle and SVC - is there a massive PE? Is there SVC obstruction?
Potential space - is there a pneumothorax or pleural effusion?
The lungs - is there pulmonary oedema or consolidation?
Interesting Blood Gas
65 yo male was found outside in the rain by his neighbours with confusion. He was hypothermic with a temperature of 29 degrees.
Look at the venous blood gas from 09:32. Consider also the other results included. What effect does temperature have on a blood gas?
Interpretation
There is a moderate acidaemia (pH 7.20). The primary problem is a metabolic acidosis as determined by a negative BE and a low bicarb if using a traditional approach.
Fencl-Stewart approach
BE is -10
SID = 136+5-90 = 51
This should be 42 therefore there is a hypochloraemic alkalosis with the expected chloride effect of +9 on the BELactate = 17. Therefore there is a lactic acidosis with the expected effect on the BE being -16
Albumin = 24. Therefore there is a hypoalbuminaemic alkalosis with the expected effect on the BE being (42-24)/4 = +4
If we add these effects together we get 9-16+4 = -3
The measured BE is -10 meaning there is another -7 (i.e. an unmeasured metabolic acidosis occurring - likely to be ketone bodies, toxic alcohols etc)Using Fencl-Stewart we have identified four seperate metabolic processes
Traditional approach
AG = 136-90-17 = 29
Therefore there is a HAGMADelta ratio = (AG-12)/(24-bicarb) = (29-12)/(24-17) = 2.4
Therefore there is a HAGMA + a metabolic alkalosis
Remember the causes of HAGMA with the acronym LTKR (Lactate, Toxins, Ketones, Renal) and the causes of metabolic alkalosis with the acronym GROE (GI acid loss, Renal acid loss, overdose of base and endocrinopathy)or, delta gap = difference between delta AG and delta Bicarb
Change in AG 34-16 = 18, Change in bicarb 26-17 = 9
Therefore there is +9 of another alkalosis (in this case likely hypochloraemia)
However the AG should be corrected for albumin, and the process then becomes a bit more complicated
So comparing Fencl-Stewart with the traditional method (and albumin corrected traditional method). The traditional method won’t acknowledge the albumin effect. It will underestimate the degree of HAGMA and doesn’t differentiate the multiple possible contributors to the HAGMA.
Other
This is a venous gas so difficult to accurately comment on the pCO2 only to say that the value is <45mmHg and therefore probably relatively accurate with the arterial value. Expected PCO2 = 1.5 x bicarb +8 = 33.5. If we were to assume the above value is accurate, this would indicate a concurrent, mild respiratory acidosis.
Low albumin is an overall poor prognostic factor
He is hypoglycaemic
The potassium level is appropriate for his pH
There is a mild raised CK, deranged LFTs, hypomagnesaemia and acute renal failure
Overall, there is a lot happening in this gas. The differential diagnoses for this patient are immense and clinical history and examination is required. Probably, the patient is an alcoholic patient who has started vomiting and stopped drinking.